Guides
Med spa operations: why a full calendar can still lose money
Med spa operations in four steps for one treatment room: count available hours, cost units drawn, place each cost line and test whether a full calendar pays.
What to take away
- A full calendar does not prove a profitable room. Revenue per treatment room is total treatment revenue divided by room-hours available, not room-hours booked.
- Cost per unit equals vial cost divided by units actually drawn, and wasted units are a real cost line.
- Injector pay, medical director fees, supply and depreciation land in different places in the P&L, and misplacing them hides the true margin on a service.
- A no-show policy only works if it is written, disclosed before booking and applied the same way to every patient.
- A device bought before demand exists becomes fixed overhead that the injectable margin has to carry.
This is business operations, not clinical, legal or tax advice. Dosing, technique and complications belong to the treating clinician and the FDA labeling for the product. Scope of practice and supervision are set by your state medical and nursing boards; confirm them with a licensed attorney.
Busy is not the same as profitable
A treatment room earns money only while a patient is in it. Everything else in the building is overhead against that hour, so the test of a room is what each available hour earns, and what that hour cost to deliver.
A calendar can look full while the room loses money, because the lines that eat the margin do not show on the schedule. The four steps below take one room through one month and show where the money goes.
Step one: count the hours you could have sold
Revenue per treatment room is total treatment revenue divided by room-hours available, not room-hours booked. The gap between those two numbers is your real capacity loss, and it is the first thing to measure.
Take a single room open 40 hours a week, four weeks a month: 160 room-hours. Suppose 96 of those hours are booked with treatments. If the room bills $38,000 in the month, revenue per room is $237.50 per available hour. The 64 unbooked hours are the number to attack first.
Revenue per room vs rebooking rate
Revenue per room
- Definition
- Revenue / room-hours available
- Capacity loss
- Available minus booked
- High + low
- Consultation-heavy book
- Pull by
- Provider, service line
Rebooking rate
- Definition
- Patients with next appointment
- Capacity loss
- Not applicable
- High + low
- Under-priced provider
- Pull by
- Provider, service line
Rebooking rate is the share of patients who leave with a next appointment already on the calendar. It is the cheapest growth metric a med spa has, because the patient is already in the chair and already trusts the injector.
Pull both numbers monthly, by provider and by service line. A provider with high revenue per room and low rebooking is running a consultation-heavy book that will not repeat. A provider with the reverse is under-priced.
Step two: cost the product by units drawn
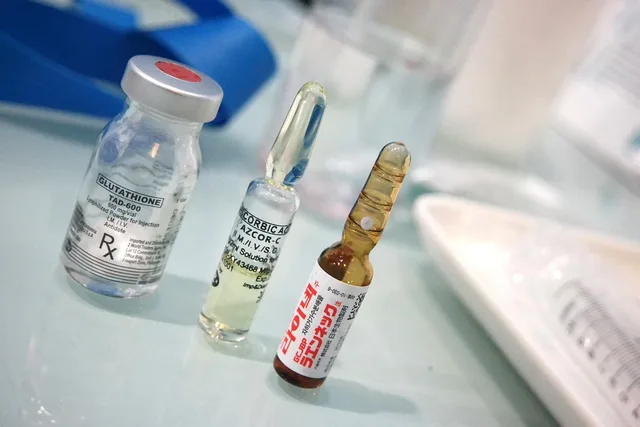
A vial has a labeled number of units, but you can bill only the units you actually draw. Those two numbers are not the same, and the gap is where injectable margin leaks.
Write it as arithmetic you fill in yourself:
Injectable unit economics math
- Cost per billed unit = (vial cost + shipping) / units drawn
- Units drawn = labeled units minus dead space, partial doses, expired vials
- Break-even price = cost per billed unit + injector time + room cost per hour
Say a vial costs $600 and the label says 100 units. Draw all 100 and cost per unit is $6.00. Draw 90 instead, from technique or from a vial that will not fully empty, and cost per unit is $6.67. On a 40-unit treatment that gap is about $27 per patient.
Track the difference between labeled units and drawn units monthly. A widening gap is a supply problem or a technique problem, and both show up as margin before they show up anywhere else.
Step three: place each cost line where it belongs
Injector pay, medical director fees, supply and depreciation sit in different places, and misplacing them hides the true margin on a service. Sort them before you judge any room.
| Cost | Behaves as | What it tells you |
|---|---|---|
| Injector pay, hourly or salaried | Cost of services, above the gross margin line | Whether a full book covers a fixed hourly cost |
| Injector pay, commission | Cost of services, charged per treatment | Whether the rate leaves margin after supply |
| Medical director fee | Fixed operating expense, flat against volume | The monthly cost of legal coverage |
| Supply: product, needles, gloves | Cost of services, charged per treatment | The true margin on one treatment |
| Equipment depreciation | Fixed operating expense, below the gross margin line | The monthly cost of a device, whether or not it runs |
Where medspa costs belong
Cost
- Supply
- Cost of goods sold
- Injector pay
- Labor or COGS
- Medical director fee
- Fixed overhead
- Room and equipment depreciation
- Fixed overhead
Where it belongs
- Supply
- Gross margin per treatment
- Injector pay
- Pays for chair time
- Medical director fee
- Monthly revenue floor
- Room and equipment depreciation
- Device pays for itself
What it tells you
- Supply
- Injector pay
- Medical director fee
- Room and equipment depreciation
How an injector is classified is not an owner's choice. It is determined by state law and by the working relationship, and getting it wrong exposes the business to back taxes, penalties and licensing complaints.
The Department of Labor says employers may consult its regulations and resources to analyze a worker's status as an employee or independent contractor, and the injector classification guide applies it to this role.
Your state board of nursing and state medical board publish the supervision and delegation rules. AmSpa maintains state-by-state summaries that are a reasonable starting point before you call a lawyer.
Records back every line. The IRS says you may choose any recordkeeping system suited to your business that clearly shows your income and expenses, so pick one that keeps each cost in its own line.
Step four: run the full-calendar test
Now put the room together. Work through the month in this order:
- Start with the month's treatment revenue from the room, which is $38,000 in the example.
- Subtract the supply cost of those treatments.
- Subtract injector pay, whether hourly share or commission.
- Subtract the room's share of the medical director fee and of equipment depreciation.
- Divide what remains by the room-hours available, not the hours booked.
If supply, injector pay, medical director fee and equipment depreciation together exceed the revenue, the room is busy and unprofitable at the same time. That failure hides behind a full calendar, because nothing on the schedule looks wrong.
The break-even formulas show how far price, drawn units or volume must move to close the gap. Change the lever that the numbers point to, and run the same five steps next month.
Protect the hours you have
Every no-show is an empty room-hour that was already counted as booked. Build the booking flow around three gates, so the slot is held and the patient is ready when they arrive.
Three gates of booking flow
- Intake before appointmenthistory, meds, allergies reviewed by clinician
- Deposit or card on file at booking, disclosed in writing
- Confirmation and reminder cadencetwo touches, one inside 24 hours
- Apply cancellation policy to every patient, including top spenders
Booking flow and no-show policy
- Intake gate. Health history, medications and contraindications are screened before the slot is confirmed.
- Deposit gate. A card on file or a deposit holds the appointment, and the cancellation terms are disclosed and accepted at booking.
- Reminder gate. Confirmations and reminders go out on a set schedule, and the patient has to reply to keep the slot.
Apply the cancellation policy to every patient, including the ones who spend the most. A policy enforced selectively is not a policy, and staff will stop defending it within a month.
Before a device takes a room-hour
The FDA regulates aesthetic devices as medical devices when their intended use brings them under that authority. Before buying one, answer three questions in writing.
Before buying an aesthetic device
Is this device cleared or approved for the indication we plan to market?
confirm cleared or approved status for intended use
do not market or buy for that indication
Equipment and who may operate
- What is the device cleared or approved by the FDA to do, and does the treatment you plan to sell fall inside that indication?
- Who on your staff may legally operate it in your state, and at what supervision level?
- What weekly volume at your price pays for the device, its service contract and its consumables, and within how many months?
The third question is where equipment purchases go wrong. A device bought before demand exists becomes fixed overhead that the injectable margin has to carry. Run the arithmetic on your own price and your own realistic weekly volume before signing.
Common questions
Why is revenue per room lower than I expected?
Because it is divided by the hours the room was available, not the hours it was booked. Compare the two counts. The gap is unbooked time, and it is the first place to look.
How do I price an injectable treatment?
Start from the vial, not the competitor's menu. Divide total vial cost including shipping by the units you actually draw, add injector time and room cost per hour, then set your price above that floor. Recheck the drawn-units figure monthly, because it moves.
Who is allowed to inject or operate a device in my state?
That is set by your state medical and nursing boards and by the device's cleared indication. Requirements differ on supervision, delegation and corporate structure. Confirm with your state boards and a licensed attorney before you build the schedule around an assumption.
How often should I review these numbers?
Monthly for revenue per room, rebooking rate, drawn units and no-show rate. Reopen pricing and equipment decisions whenever supply cost, injector pay, the medical director agreement or your state's rules change.
What should a new owner avoid?
Buying a device before demand exists, pricing from a competitor's menu instead of vial yield, and enforcing the cancellation policy only against patients who are easy to say no to. Each one is cheap to fix early and expensive to fix later.